Friday, March 17, 2023

Bill to address postpartum depression and other maternal mental-health problems has passed and awaits the governor's action

By Melissa Patrick
Kentucky Health News

A bill to ensure greater access to information and resources for mental-health care before and after the birth of a child passed without dissent in both houses of the General Assembly and has gone to Gov. Andy Beshear.

Sen. Shelley Funke Frommeyer
"Kentucky, sadly, has one of the worst maternal mortality rates in the country," the bill's sponsor, Sen. Shelley Funke Frommeyer, R-Alexandria, told the Senate Families & Children Committee in February.  "And we're looking to get upstream of that. We really want to work towards a solution." 

Senate Bill 135 calls on the state Cabinet for Health and Family Services to create written information on perinatal mental-health disorders, including postpartum depression, and make it available on its website. It also requires the cabinet to provide access to online clinical assessment tools to help providers detect the symptoms of perinatal mental-health disorders. 

The cabinet is also charged with creating a panel of maternal- and infant-health experts to explore the issue of perinatal mental-health disorders, including prevention, treatment and gaps in service.  The panel is required to report its findings to the Interim Joint Committee on Health, Welfare and Family Services and the Advisory Council for Medicaid Services on or before Nov. 1 of each year. 

"This bill is simple, but the impact will be wide reaching and could mean the difference between life and death for some Kentucky mothers," said Rep. Stephanie Dietz, R-Edgewood, who carried the bill in the House.

Amendment for pediatric recovery centers

A House floor amendment that included language from House Bill 436 was added to the bill and agreed to in the Senate. It directs the cabinet to submit a state plan amendment application by Nov. 1, 2023 to the federal Centers for Medicare and Medicaid Services to provide medical assistance "to the fullest extent permitted under federal law" for inpatient and outpatient services provided by a residential pediatric recovery center. 

Rep. Matt Lockett, R-Nicholasville, sponsor of HB 436 and the amendment, told the House that there is a great need for these centers because they care for babies with neonatal abstinence syndrome, noting that Kentucky has 15 babies born with NAS per 1,000 births. 

"These centers provide a unique non-hospital holistic approach that saves taxpayer dollars by avoiding expensive hospital stays and unnecessary foster care placements," said "They provide high quality inpatient medical care in a home like setting for babies born exposed to addictive substances."

Ernie Scott of Letcher County dies of rare brain aneurysm at 46; had been director of the State Office of Rural Health since 2013

Ernie Lee Scott
Funeral services were held Friday for Ernie Scott, who was director of the State Office of Rural Health in the University of Kentucky Center of Excellence in Rural Health. He did Sunday, March 12, at his home in Partridge, in Letcher County. He was 46.

The cause of death was a "random and rare" aneurysm in the brain, Coroner Perry Fowler told The Mountain Eagle of Whitesburg.

Scott started his career as a radiology technologist, earned a bachelor’s degree in health care administration at Midway College, was director of planning and special projects for Mountain Comprehensive Health Corp. in Whitesburg, and became director of the Office of Rural Health in 2013.

In 2014 Scott received the Emerging Leader Award from the National Organization of State Offices of Rural Health, and in 2020 he won the Kentucky Rural Health Association's Dan Martin Award for lifetime contributions to rural health. Last year, the office was one of three organizations in the nation to receive a three-year, nearly $900,000 grant from the federal Office of Rural Health Policy to improve access to health care for veterans living in rural Kentucky and to improve coordination of veterans' care.

Scott is survived by his wife, Tiffany Bullock Scott, and their daughter, Addyson Grace Scott. The couple owned and operated the General Store at Pine Mountain Crossing on US 119 and ran a hospital gift shop. Other survivors include his mother, Iris Jean Scott; siblings Howard Wayne Scott (Renee) and Sherry Scott Geiger (David); and many nieces and nephews.

"To know Ernie was to love him," his obituary says. "He quickly became a friend to all he met. He always greeted folks with a smile and often a big hug. He was a planner, a goal setter, and achiever. He loved his family, friends, church, and his community. He poured his heart and soul into Letcher County (specifically Cumberland River) and made huge impacts in many other rural communities."

His funeral was at Lewis Creek Pentecostal Church, along the Poor Fork of the Cumberland River in Partridge, with burial in the D.L. Creech Cemetery four and a half miles downstream, at Cumberland. Tri-City Funeral Home was in charge. Memorial donations may be made to a health-care scholarship fund in Scott’s name at Commercial Bank, 1701 E. Main St., Cumberland KY 40823.

Medical cannabis bill passes Senate, awaits House vote March 30

By Melissa Patrick
Kentucky Health News

A bill that would make medical marijuana legal for some in Kentucky has passed the state Senate for the first time and awaits a vote in the House, which has passed two similar bills in previous legislative sessions.

Sen. Stephen West
"It is time for Kentucky to join the other 37 states in the United States that allow medical marijuana as an option for their citizens," said Sen. Stephen West, R-Paris, in presenting his bill to the Senate, adding later, "It is understood that this is a very complex issue and if passed, will be a work in progress." 

Senate Bill 47 passed late Thursday night on a 26-11 vote. The House gave the bill its first of three required readings the same night, which will allow enough time for it to pass out of the House when the lawmakers return March 29 and 30.

Last year, after a House-passed bill again got no hearing in the Senate, Gov. Andy Beshear used his pardon power to allow people with 21 specified medical conditions and a doctor's certificate to possess up to eight ounces of marijuana bought legally in another state. (Illinois is the only adjoining state where nonresidents can legally buy cannabis.) Beshear signaled Thursday that he would sign the bill.

West, who said he has worked on such legislation for about five or six years, told the Senate, “This is one of those issues where you take out the ledger and you list the pros and cons. It’s a long list on both sides, but for me personally, the pros outweigh the cons.”

The 124-page bill would not allow medical marijuana to be smoked, require users to be 18 or older or be a caretaker for a child, limit supply, and not take effect until Jan. 1, 2025.

The medical marijuana would be allowed for certain "qualifying medical conditions," including all cancers regardless of the stage; chronic, severe, intractable or debilitating pain; epilepsy or any other tractable seizure disorder; multiple sclerosis, muscle spasms or spasticity; chronic nausea or cyclical vomiting syndrome that has proven resistant to other conventional medical treatments; post-traumatic stress disorder; and any other medical condition or disease for which the new Kentucky Center for Cannabis Research at the University of Kentucky determines would benefit from medicinal marijuana.

West and other lawmakers praised the advocacy of Eric and Michelle Crawford, a quadriplegic who has long searched for another option to manage his pain. They also praised the ongoing work of advocate Jamie Montalvo, who suffers from multiple sclerosis, toward getting this bill passed. 

 Sen. Phillip Wheeler, R-Pikeville, said the Crawfords and Montalvo don't want to break the law: "These are people that are willing to work hard and make sacrifices to comply with the law. What they are looking for is a pathway forward to make sure that people can get a safe product." 

Sen. Stephen Meredith, R-Leitchfield, said it was important to show those who are suffering from  debilitating diseases  "just a little bit of mercy" and that was why he voted yes.   

“Will this be abused by some folks?  It certainly will," he said. "But again, if we can benefit just one person, one child, I think it’s worthwhile."

Only Republicans voted against the bill: Gary Boswell of Owensboro, Danny Carroll of Benton, Donald Douglas of Nicholasville, Rick Girdler of Somerset, President Pro Tem David Givens of Greensburg, Chris McDaniel of Ryland Heights, Robby Mills of Henderson, John Schickel of Union, President Robert Stivers of Manchester, Mike Wilson of Bowling Green, and Max Wise of Campbellsville. 

Marijuana is a "scourge of the earth," Boswell said. "I urge my colleagues to vote no. If you are going to violate federal law, at least tighten up the bill to include only the critically ill." 

Douglas, a physician, said, “With the different growing techniques and the increased concentration of these chemical compounds, I’m not really convinced that this drug is safe. But we do have some research going on out there, and I really want to thank the University of Kentucky. I hope we have some other institutions doing research who will give us good information.”

Bill to ban gender-affirming care for youth passes after advocates scramble and maneuver to quash bipartisan Senate changes

UPDATE, March 24: Beshear vetoed the bill.

By Melissa Patrick
Kentucky Health News

A revised bill with language to ban gender-affirming care for Kentucky's transgender youth moved quickly through both houses of the General Assembly Thursday and is on Gov. Andy Beshear's desk.

Even if the Democratic governor vetoes the bill, as is expected, the supermajority of Republicans in the legislature can override the veto when they return on March 29 and 30. 

Changes made to Senate Bill 150, sponsored by Sen. Max Wise, R-Campbellsville, were approved in a hastily called meeting of the House Education Committee, which approved it 16-5 with Republican Rep. Killian Timoney of Nicholasville voting "no" with the four Democrats on the committee.

Soon after, the amended bill passed the House 75-22, despite more than two hours of Democrats speaking against it.

SB 150 moved quickly to the Senate for concurrence with the House changes. It passed 30-7 to shouts and obscenities yelled from the gallery at legislators. Sen. Danny Carroll of Benton was the only Republican to vote against the bill and Sen. Robin Webb of Grayson, was the only Democrat for it.

The night before, Carroll had narrowly succeeded in watering down a House bill that would limit gender-affirming care, but after his floor amendment passed 19-17 the Senate laid HB 470 on the clerk's desk and Wise worked with the House to put most of the original bill into SB 150.

The amended version of SB 150 prohibits gender-affirming medical care for trans youth, including gender-affirming surgery or puberty-blocking hormones. It allows health-care providers to de-transition youth who are already taking such hormones, which would require them to taper them off of the drugs. It also provides exemptions for youth who have a diagnosed sexual-development disorder. 

Providers who violate the law would have their licenses revoked, and youth who claim injury as a result of gender-affirming care could fule suit to recover damages until they turn 30 years old or within three years from the time they discovery the injury. The normal deadline for a lawsuit is one year.

SB 150 also includes its original provisions to prohibit schools from requiring teachers to use a trans student's preferred pronouns and requires schools to notify parents about any content related to sexuality. It also added content from HB 177, which does not allow any sex education to children in grades five and below and bans all students from receiving instruction that explores "gender identity, gender expression or sexual orientation."

Carroll speaks on SB 150. (Legislative Research Comm. photo) 
Carroll's revised bill likewise prohibited surgical medical treatments for trans youth, but unlike allowed some nonsurgical medical-treatment options. His change was supported by all seven Democratic senators and 12 of the 30 Republicans. Seven of them voted the other way when Wise's bill came back from the House. It passed 30-7.

Republicans who voted with Carroll on his amendment but against him on the SB 150 were Jared Carpenter of Berea, Matthew Deneen of Elizabethtown, President Pro Tem David Givens of Greensburg, Jason Howell of Murray, Amanda Mays Bledsoe of Lexington, Chris McDamiel of Ryland Heights, Stephen Meredith of Leitchfield, Mike Nemes of Louisville, Brandon Smith of Hazard, Brandon Storm of London and Whitney Westrefield of Fruit Hill (Christian County). 

Westerfield said his yes vote was "reluctant." He said SB 150 was better than HB 470 largely because it allows doctors to talk freely with their patients about their medical concerns without fear of liability.  

Carroll, explaining his no vote, said, "We know that most kids that are struggling with gender dysphoria decide to stay the gender that they are. It's a phase that they go through, [and for] some it's not. What would it hurt to allow doctors to have access to these puberty blockers to give these kids time to work through the issues that they face? Why can't we trust our doctors, as we do for every other issue, to guide us through these things?"

Sen. Karen Berg, D-Louisville, whose trans son Henry died by suicide in December, said of SB 150, "This is absolutely willful hate for a small group of people that are the weakest and most vulnerable among us."

During the House floor debate, Rep. Chad Aull, D-Lexington, reminded the lawmakers that nearly half of LGBTQ individuals have seriously considered suicide and that percentage is much higher with transgender children. "If this legislation causes one child in Kentucky to consider or to take their own live, this is a wrong piece of legislation," he said.

Terry Brooks, executive director of Kentucky Youth Advocates, issued a statement calling the speedy passage of SB 150 "parliamentary shenanigans" and that the genesis of the measure "springs from a national agenda of fearmongering."   

"Passage of SB 150, even with the amendment, means that kids lose access to much needed health and mental health supports. It means that families lose vital rights. And it means that Frankfort Republicans – save the courageous Representatives Banta, Dietz, Moser, and Timoney and Senator Carroll, who refused to vote in support of the measure – lose their long-held core governing identity. That is a lose-lose-lose trifecta for us all," he said. 

Senate Majority Floor Leader Sen. Damon Thayer, R-Georgetown, who voted for the bill, said SB 150's anti-trans provisions were modeled after a law in South Dakota. 

Rep. Kim Moser, R-Taylor Mill, while explaining her "pass" vote said, "I'm concerned that it doesn't comment enough on the mental-health treatment. . . . I really would like to see that we are allowing for mental-health treatment, watchful waiting and making sure that we're supporting the families who are going through this issue. I'm passing today because we want to protect children on all sides of this issue." Moser is chair of the House Health Services Committee.

Tamarra Wieder, state director for Planned Parenthood Alliance Advocates, voiced her disappointment: "SB 150 is deliberately designed to create a culture war across this commonwealth. It has nothing to do with parental rights. It has nothing to do with caring for kids. What it does is go against the guidance of every major medical association in this state. It replaces our physicians with politicians and places our trans kids' lives on the line." 

Thursday, March 16, 2023

Transgender bill awaits a vote in the Senate after an unusual bipartisan vote waters it down; outcome remains uncertain

UPDATE, 6:50 p.m. March 16: The Senate agreed to the changes made to Senate Bill 150 and passed it on a vote of 30-7. It now goes to Gov. Andy Beshear's desk for his consideration. 

UPDATE, 4:44 p.m. March 16: The House passed Senate Bill 150 with an amendment that included some of the provisions of  House Bill 470 on a vote of  75-22  It now goes to the Senate for concurrence or non-concurrence. 

UPDATE, 1:55 p.m. March 16: A House committee approved a substitute Senate Bill 150 that keeps some of the House-passed provisions of House Bill 470. If passed by the House the revised SB 150 could become the vehicle for House-Senate negotiations later today. The Lexington Herald-Leader has a story.

By Melissa Patrick
Kentucky Health News

The state Senate voted 19-17 Wednesday night to water down a House bill that would limit gender-affirming medical care for Kentucky's minors, but a vote on the revised version was delayed until Thursday. 

Sen. Danny Carroll
House Bill 447, sponsored by Rep. Jennifer Decker, R-Waddy (Shelby County), was called up for a vote with five floor amendments proposed. All but Floor Amendment 2, submitted by Sen. Danny Carroll, R-Benton, were withdrawn.

Carroll's wide-ranging amendment got the votes of 12 of the 30 Republican senators and all seven of the chanber's Democats. The Republican majority generally does not advance bills that are not supported by most Republican senators.

Senate President Robert Stivers, who voted against the bill, told the Lexington Herald-Leader that he couldn't predict what the Senate would do on the issue. “I think there was a lack of knowledge as to what all the amendments in the subject matter meant,” he said. “This is not the easiest of subject-matter topics.”

Like Decker's bill, Carroll's measure still prohibits surgical medical treatments for trans youth. However, it would allow some nonsurgical medical treatment options with the consent of the child's parent or legal guardian.

In order to qualify for the nonsurgical medical treatment, the child must have a medical diagnosis of gender dysphoria and the treatment must be provided by a licensed physician who is appropriately trained and experienced in providing it. It also calls for the child to be under the care of a clinical psychologist or psychiatrist. 

The revised bill defines which reversable puberty-blocking drugs are allowed and says treatment shall not include cross-sex hormones, like testosterone or estrogen, in amounts that are larger or more potent that would naturally be found in a healthy person of the same age and sex.  

It says all care must meet evidence-based medical standards for treatment of children with gender dysphoria and include mental-health services that address a  person's sex or gender but don't promote gender transition. 

Carroll's amendment removed the original bill's provisions that would have blocked a transgender youth from legally changing their name or birth certificate. It kept in place language from two bills that were added in a Senate committee: Teachers would not be required to use a student's preferred pronouns, and parents would gain more say about sex education and discussions about sexual orientation in schools would be prohibited. 

Besides Stivers, others voting against the amendment were Republican Sens. Gary Boswell of Owensboro, Donald Douglas of Nicholasville; Shelley Funke Frommeyer of Alexandria; Rick Girdler of Somerset; Jimmy Higdon of Lebanon, Robby Mills of Henderson, John Schickel of Union, Adrienne Southworth of Lawrenceburg, Damon Thayer of Georgetown; Lindsey Tichenor of Smithfield; Johnnie Turner of Harlan; Stephen West of Paris; Phillip Wheeler of Pikeville; Gex Williams pf Verona; Mike Wilson of Bowling Green, and Max Wise of Campbellsville. 

If the Senate passes the amended bill on Thursday, that will give the chambers a few hours to work out their differences and send the bill to the governor's desk ahead of the veto period. Democratic Gov. Andy Beshear is expected to veto the bill if he gets it. The supermajority of Republicans could easily override a veto, but only if the bill gains final passage on Thursday.

Even before the latest overhaul of the bill made in the Senate, the bill had already undergone several changes. 

The bill that passed out of the House on a 75-22 vote would have banned any treatment that supported gender transition for Kentucky's minors, including puberty-blocking hormones and gender re-assignment surgery. It also included a 30-year window for lawsuits against health-care providers who provided any gender-affirming care to minors, among other things. Changes from the original bill that were made in committee removed mental health care providers from the list  of providers who couldn't treat youth seeking gender affirming care.

The Senate Families and Children Committee added more changes to the bill March 14, including the addition of Senate Bill 150, sponsored by Sen. Max Wise, R-Campbellsville, which prohibits schools from requiring teachers to use a trans student's preferred pronouns and requires schools to notify parents about any content related to sexuality. It also included content from HB 177, sponsored by Rep. Shane Baker, R-Somerset, which does not allow any sex education to children in grades five and below and bans all students from receiving instruction that explores "gender identity, gender expression or sexual orientation." These changes remained in Carroll's amended version of the bill. 

The amended bill passed out of the committee 6-3. Carroll and fellow Republicans Whitney Westerfield of Fruit Hill (Christian County), Julie Raque Adams of Louisville voted "yes" but called for significant changes in the final version.

“I’m extremely uncomfortable putting myself in the place where a doctor should be. I don't have the training. I don't have the knowledge to make decisions,” said Carroll. “However, I feel a complete obligation to protect our kids. I too don't like the bill. I hate the tone of the bill. I think we could have accomplished what we needed to accomplish without going so far." 

Wednesday, March 15, 2023

Medical marijuana passes Senate committee, awaits floor vote

L-R: Eric Crawford, Jamie Montalvo, Sen. Stephen West and Chris Joffrion spoke in favor of West's medical marijuana bill in the Senate Licensing and Occupations Committee. (Legislative photo)  
By Melissa Patrick
Kentucky Health News

For the first time, a bill to legalize and regulate medical marijuana in Kentucky has cleared a Senate committee after years of the idea being stalled in the upper chamber. 

Senate Bill 47, with a committee substitute, passed out of the Senate Licensing & Occupations Committee March 14 on an 8-3 vote. Republican Sens. Donald Douglas of Nicholasville, Committee Chair John Schickel of Union, and Chris McDaniel of Ryland Heights, cast the "no" votes. 

Senate Majority Floor Leader Damon Thayer of Georgetown, a long-time opponent of medical marijuana legislation, was among those voting in favor of the bill, saying he approved its narrow focus and that his support was for "the sake of those who suffer." 

The 124-page bill, sponsored by Sen. Stephen West, R-Paris, does not allow medical marijuana to be smoked, requires users to be 18 or older or be a caretaker for a child, and would not take effect until Jan. 1, 2025.

The medical marijuana would be allowed for certain "qualifying medical conditions," including all cancers regardless of stage; chronic, severe, intractable or debilitating pain; epilepsy or any other tractable seizure disorder; multiple sclerosis, muscle spasms or spasticity; chronic nausea or cyclical vomiting syndrome that has proven resistant to other conventional medical treatments; post-traumatic stress disorder; and any other medical condition or disease for which the new Kentucky Center for Cannabis Research determines would benefit from medicinal marijuana. 

Longtime advocate for medical marijuana Eric Crawford of Mason County, who has been a quadriplegic for nearly 30 years, said marijuana improves the quality of his life and that he and others who benefit from it "deserve legal access without the worry of law enforcement."  

“It allows me longevity and a better quality of life. It allows me to be a better husband, son, friend and man than a pharmaceutical route. Surely there’s nobody on this committee that thinks I’d be better off taking opioids,” he said.

Sandra Marlowe, the sister of Sen. Gex Williams, R-Verona, who is wheelchair-bound due to the debiliating and deadly disease ALS, also asked the committee members to pass the bill. 

“This disease will take my life. I ask that my days be as comfortable as possible with access to the THC tincture. That is the only thing that gives me relief. . . . Without painful cramps, I am more productive," she said. 

Thayer told the Lexington Herald-Leader on Tuesday that the bill had time to get its two required readings for a vote on the Senate floor Thursday, the final legislative day before the veto session. However, he added that he's not sure it has the Senate floor votes to get passed.

If the Senate passes the bill Thursday and gets a reading in the House, the House coulld pass it when the lawmakers return for the last two days of the session, usually reserved fro veto overrides. Medical marijuana bills have passed out of the House twice.

Two people spoke against the bill: Michael Johnson of the Family Foundation and Gene Cole of the Kentucky Ethics League/ Kentucky League on Alcohol, Gambling Problems and Substance Use Disorder. 

Johnson said the while he is sympathetic to people who have not found relief from their ailment from modern medicine,  there is "insufficient scientific evidence that marijuana is an effective pain relieving agent or that it is safe and effective as a medicine." He also called for "more research"  before it is legalized.

Tuesday, March 14, 2023

Long Covid update: There's still reason to avoid Covid-19, even if you've had it already; it's 'annoyingly stubborn,' expert says

By Katelyn Jetelina
Covid-19 is not the common cold. Here’s an effort to keep you up to date on long-Covid developments.

What we knew: Long Covid after first infection was clearly a risk. The risk of long Covid after re-infection was not known.
New info: In the U.K., risk of long Covid dropped after second infections compared to first infection (4% → 2.4%). This is good and bad news: Risk drops, but risk is clearly not zero.
Why it matters: There is still reason to avoid Covid-19, even if you’ve had it already.

Metformin may work

What we knew: About 300 clinical trials are testing treatments for long Covid-19, including Metformin. Results are trickling in.
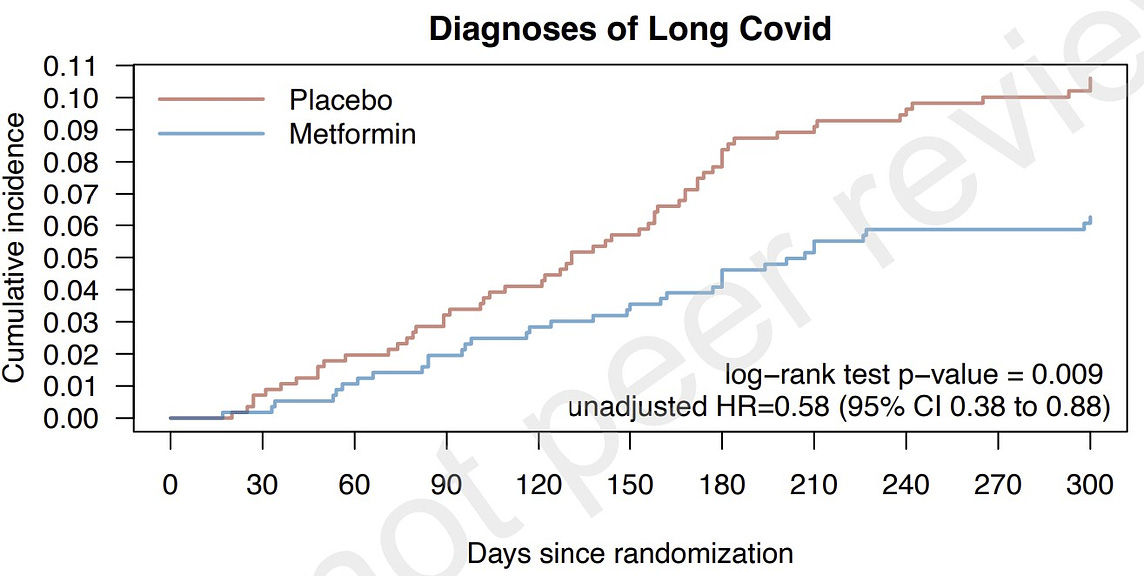
Cumulative incidence curve of long-Covid diagnoses over
10 months after randomization. Source: 
Lancet preprint.
New info: Metformin reduced long Covid in a large randomized control trial.
Metformin had a 42% reduced risk in long Covid cases compared to the placebo; 63% reduced risk if taken within four days of symptoms.
For every 100 people who took the drug, four fewer cases of long Covid nine months after infection occurred. Ivermectin and fluvoxamine had no impact.
Why it matters: People should consider Metformin, especially women who are at higher risk for long Covid. It’s best taken within four days of infection. This is a challenging timeframe in the U.S. medical care system, though.

Paxlovid may help… a little?
 
What we knew: Paxlovid helps reduce severe disease by 50-90%. We didn’t know if it helped with long Covid, though.
New info: Paxlovid reduced risk of long Covid by 26%, regardless of vaccination status and history of prior infection. We need more studies, particularly among young people, as Paxlovid’s effect will likely increase among younger people.
Why it matters: There may be small, proxy benefits from taking Paxlovid, including among younger populations that aren’t “eligible.”
 
Long Covid is annoyingly stubborn

What we didn’t know: We didn’t know the longevity of severe symptoms.
New info: Among those with long Covid, the rate in which symptoms affected daily life decreased from 45% → 25% over seven months.
Why it matters: If you get severe long Covid, there is a chance that symptoms will get better after seven months. Then again, there’s a chance that they won’t.

Still not convinced?

What we know: People living with long Covid report profound stigmatization because people disbelieve that long Covid is a “thing.”

New info: A community member of this newsletter, Dianna Cowarn (also known as Physics Babe on YouTube), was diagnosed with long Covid last summer. Her crew made a 4-minute video. Check it out here if you’re still not convinced. It’s painstaking [and is preceded by commercials].


Bottom line: Covid-19 infection is not the common cold for some. Our knowledge is inching closer to treatments. But with so much unknown, we still need to emphasize prevention—keeping Covid-19 cases low and ensuring vaccination.

Katelyn Jetelina (MPH, PhD) is an epidemiologist, data scientist, wife, and mom of two little girls. She works at a nonpartisan health policy think tank and is a senior scientific consultant to the CDC and other organizations.

How health-care providers can help prevent overdoses: 4 steps, plus culture change to make intervention routine, lessen stigma

Recommendations to health-care providers to prevent drug overdoses (JAMA Internal Medicine)

By Drs. Scott E. Hadland and Evan Wood; and Eri D. Solomon
Opinion article published in JAMA Internal Medicine

North America is experiencing an unprecedented opioid overdose epidemic now driven by illicitly manufactured fentanyl, which has largely displaced prescription opioids and heroin in most drug markets. In the context of high and rising overdose deaths, four proven clinical interventions should constitute a set of “universal precautions” that clinicians and health systems could implement to reduce opioid overdose deaths among at-risk patients, including all patients who use opioids or who may be inadvertently exposed to fentanyl.

The concept of universal precautions originally emerged as a standard approach to prevent infectious disease transmission in health care settings, and the concept has often been extended to other areas of clinical care. While failure to adopt these universal precautions with opioid prescribing may provide important lessons, a success story is the progress in addressing the HIV epidemic among people who inject drugs. Such progress was made possible through recommendations for the universal delivery of a well-defined suite of interventions including sterile-syringe provision, addiction treatment, and antiretroviral therapy.

A universal-precautions framework is overdue for people at risk of opioid overdose. Individuals who present for care with consequences of opioid use have extremely high rates of recurrent overdose and subsequent death. Critically, they may also have frequent contact with health-care settings, presenting to primary and subspecialty care (such as infectious-disease clinics), mental-health facilities, and emergency departments. Rather than demonstrating a positive association of these contacts with health outcomes, studies show that people who use drugs often experience entrenched stigma and rarely receive potentially life-saving interventions.

We view four clinical interventions as highly suited for inclusion in a suite of universal overdose-prevention interventions.

Medication-assisted treatment: First, timely provision of buprenorphine, methadone, or extended-release naltrexone should be offered as a first-line intervention for individuals who wish to receive medications for opioid use disorder (OUD). Presently, as few as one in five eligible patients receives medication, and despite clear evidence supporting buprenorphine initiation as a service provided by clinicians in emergency departments, where many individuals at risk of overdose present to receive care for drug-use–related complications, this intervention is unavailable in most hospitals. Policymakers in the U.S., including the leadership of the White House Office of National Drug Control Policy, recently called for scaling up routine access to OUD medications, and highlighted systems-level changes that are needed, including improving addiction education for clinicians, creating new and compassionate “low-threshold” clinic models that offer same-day treatment initiation and flexible scheduling, and reducing stigma. This remains an urgent medical priority in need of a comprehensive yet simple guiding framework.

Availability of naloxone: Clinicians and health systems should routinely distribute the overdose reversal medication naloxone to people at risk of overdose. Despite naloxone being remarkably effective at reversing opioid toxicity, recent investigations have shown dismally low health-system provision. In a 2019 U.S. study of commercially insured people with OUD who experienced an overdose, less than one in 20 was prescribed naloxone. Naloxone is typically covered by insurance, and in many settings can be distributed directly to at-risk patients without a prescription using supplies from local health departments and community organizations. Clinical and social support services for people at risk of opioid overdose must begin to view providing naloxone, alongside brief education on its correct use, as the standard of care.

Take-home fentanyl strips: While changes to drug paraphernalia laws may be required in some jurisdictions [including Kentucky, where one is in process], clinicians and health systems should offer take-home fentanyl test strips. Many overdose deaths result from inadvertent fentanyl exposure among individuals not intending to use potent opioids, including those who believe that they are using a different drug (eg, cocaine), prescription pills, or heroin that does not contain fentanyl but in fact does. Test strips, which can assess for the presence of fentanyl in drugs, are inexpensive and increasingly provided free of charge through local health departments. While educational efforts to support clinician understanding of the value of harm reduction programming will be essential, frontline clinicians are well positioned to provide this simple intervention to those at risk of overdose.

If you inject drugs, don't do it alone: Clinicians should offer brief education to increase awareness of underused overdose prevention strategies. Even though injecting alone is one of the most prevalent modifiable risk factors for death from overdose, many people who use fentanyl do so by themselves. Clinicians should counsel people who use drugs to avoid using them when they are alone so that someone is available to administer naloxone and call emergency services if needed, and suggest other strategies to reduce fatal overdose, including starting with only a small amount of a drug to assess its potency and avoiding mixing opioids and other sedatives such as benzodiazepines and alcohol.

To implement and scale overdose-prevention interventions across North America’s health-care settings, clinical support tools (such as standardized order sets) as well as culture change will be needed. Specifically, clinicians and health systems must address stigma against people who use drugs, recognize OUD as a medical illness, and view offering overdose prevention as central to care for people who use drugs. Applying a universal-precautions framework could help drive this culture change by clearly and simply stating what standard interventions every clinician should offer in every interaction with a person at risk of overdose.

To be sure, the above-mentioned suite of overdose-prevention strategies is not the only intervention clinicians should offer to people at risk of overdose. Nevertheless, in the context of rising mortality and risk of overdose among people who use opioids, we propose that the messaging on universal precautions should initially focus on routinely offering interventions clearly poised to alter ongoing high rates of overdose death. Additionally, clinicians should prevent the onset of medically caused OUD by avoiding inappropriate opioid prescribing (such as for mild acute pain and many types of chronic pain).

We believe that, given the remarkable ongoing discordance between overdose-prevention interventions and service delivery, the definition of a suite of evidence-based interventions and education in support of clinical culture change are long overdue and should be prioritized so that health systems may apply these universal precautions to close the implementation gap for overdose prevention.

Monday, March 13, 2023

Legislature passes bill to keep Kentuckians' disabilities from being sole cause of discrimination in allocating organs for transplant

Centers for Disease Control graphic
By Melissa Patrick
Kentucky Health News

A bill to ensure that Kentuckians with disabilities are not discriminated against when being considered for an organ transplant has passed both houses of the General Assembly and is on its way to the governor's desk.

House Bill 238, sponsored by Rep. Wade Williams, R-Earlington, would prohibit a health-care provider from discriminating against an individual who has a disability, based solely on the disability, when determining their eligibility for an organ transplant.

Williams told the House Families and Children Committee March 2 that HB 238 doesn't tell providers that they can't consider the disability at all for an organ transplant, but that they can only consider it if it is "medically significant."

The bill also directs health-care providers to consider a person's personal-care support when making a decision about organ transplants. It also allows a person with a disability to file suit for relief via an injunction if they believe that a provider has violated the legislation.

On March 13, Morgan Elliston of Frankfort, told the Senate Families and Children Committee that her daughter Quinn, 11, has a rare genetic disorder, Wolfe-Hirschhorn Syndrome, that has caused  growth and intellectual disabilities, epilepsy and chronic kidney disease.

Elliston said Quinn's kidneys are functioning at 30 percent and chances are slim that she will not need a kidney transplant in the future.

"All across the commonwealth, individuals like Quinn may someday need an organ transplant," said Elliston. But as written, she said, current guidelines offer no protections for people with disabilities. She quoted from them:  "Allocation of a deceased donor organ must not be influenced positively or negatively by political influence, national origin, ethnicity, sex, religion or financial status -- no mention of disabilities."

Elliston said 37 states have passed similar legislation. "With the passing of House Bill 238, you will be giving individuals with disabilities the same rights as every other individual that needs a transplant," she said.

The House bill passed the bill 98-0 March 7; the Senate passed it March 13 on the consent calendar, which is used for bills that are unanimously approved in committee.

Bill to require insurers to cover biomarker testing goes to Beshear

UPDATE, March 23: Gov. Andy Beshear has signed the bill into law.

MD Anderson Cancer Center graphic
By Melissa Patrick
Kentucky Health News

A bill to require private and public insurance plans in Kentucky to cover biomarker testing for cancer and screenings for genetic-based reactions to drugs has finally passed and is on its way to Gov. Andy Beshear. 

House Bill 180, sponsored by Rep. Kim Moser, R-Taylor Mill, will require all private insurance plans, Medicaid and the state-employee health plan to cover the biomarker and pharmacogenetic tests when they are medically necessary.

Pharmacogenetic testing determines how a patient will respond to medication. Biomarker testing “is a way to look for genes, proteins, and other substances (called biomarkers or tumor markers) that can provide information about cancer. Each person’s cancer has a unique pattern of biomarkers,” says the National Cancer Institute.

Senate President Robert Stivers, R-Manchester, who carried the bill in the Senate, said he took it off the consent calendar, used to pass groups of non-controversial bills without a roll call, so senators and the public could become more aware of the bill's contents.

Stivers explained that biomarker testing allows for the targeted treatments of cancers, instead of a one-size-fits-all treatment for everyone. This "gives that individual a higher likelihood of being successful," he said. "As we become more technologically advanced, this is the direction that we hope medicine goes." 

Stivers said that while this bill is an insurance mandate, something the legislature traditionally resists, its financial analysis shows that it will have a minimal cost. The Kentucky Department of Insurance said it did not expect the bill to materially increase premium or administrative costs for fully insured health plans. Tt did not analyze the impact on Medicaid or the state-employee health plan. 

Sen. Danny Carroll, R-Benton, told the Senate members that he, his wife and his daughter, who has cerebral palsy, had recently undergone genetic testing to determine if his daughter would be a good candidate for a specific type of surgery, and learned that she was.

Carroll, who is president and CEO of Easterseals West Kentucky, also said pharmacogenetic testing is especially important for people with intellectual disabilities because it helps to determine which medicines work best for them: "This could very well change their life and the quality of life that they're able to live."

The American Cancer Society Cancer Action Network applauded the passage of the bill, noting that private health insurance and Medicaid coverage of biomarker testing have not kept pace with the rate of innovation.

“Dubbed ‘the right treatment at the right time,’ precision medicine has played a critical role in improving cancer outcomes,” Doug Hogan, government relations director for ACS, said in a news release. “Over 30,000 Kentuckians will be diagnosed with cancer this year. Ensuring patients who could benefit have access to insurance-covered biomarker testing to help identify the most appropriate treatment gives them a better quality of life and the best chance of survival.”

HB 180 passed the House 97-0 Feb. 22 and the Senate 34-0-1 March 13. Sen. Adrienne Southworth, R-Lawrenceburg, cast a "pass" vote.

New coronavirus cases dropped in Ky. last week but Covid-19 deaths increased; N.Y. Times ranks new-case rate 2nd in nation

New York Times map reflects the paper's ranking of Florida and Kentucky as 1-2 in new-case rates.
By Melissa Patrick
Kentucky Health News

Kentucky reported a 46 percent drop in new coronavirus cases last week, but its rate of new infections remained among the highest in the nation. 

The state Department for Public Health reports that there were 2,572 new cases of the coronavirus last week, or 367 cases per day. That's down 45.6% from the 4,736 cases reported in the prior week's report. 

The weekly new-case rate was 6.39 cases per 100,000 residents, down from 7.99 the week prior and 9.23 the week before that. The top 10 counties were Bath, 18.29 cases per 100,000; Adair, 17.86; Rockcastle, 17.11; Clinton, 16.78; Webster, 12.14; Morgan, 11.81; Rowan, 11.68; Floyd, 11.64; Russell, 11.16; and Montgomery, 11.16.

Despite the continued decline on the state report, The New York Times ranked Kentucky's seven-day new-case rate second in the nation, behind Florida. The Times reports that Kentucky has seen a 41% increase in cases in the last two weeks. The discrepancy could stem in part from Union County, which the Times says has a rate of 81 per 100,000. The county is home to a federal Job Corps center, and federal facilities generally do not report Covid-19 cases to the state.

The state attributed 47 more deaths to Covid-19 last week, up from 13 the week prior. The state's pandemic death toll is now 18,177.

Sunday, March 12, 2023

FDA proposes new requirements for makers of tobacco products aimed at minimizing contamination, protecting public health

American Heart Association photo illustration
By Melissa Patrick
Kentucky Health News

The U.S. Food and Drug Administration is proposing new rules that are aimed at minimizing contamination of tobacco products, including electronic cigarettes, and that would create manufacturing specifications to ensure product consistency. 

“While no tobacco product is safe, this proposed rule is intended to minimize or prevent additional risks associated with these products,” Brian King, director of the FDA’s Center for Tobacco Products, said in a news release. “Once finalized, it would establish requirements for tobacco product manufacturers that will help protect public health.”

The proposed regulations aim to see that tobacco products are made according to established specifications and would require manufacturers to take appropriate measures to prevent contamination of the product. 

One regulation says companies that create products that don't meet those specifications will be investigated and be required to institute appropriate corrective actions, such as a recall. 

Another establishes the ability to trace all components or parts, ingredients, additives and materials, including by batch of the finished product, to aid in such investigations. 

"These requirements would help minimize or prevent the manufacture and distribution of tobacco products contaminated with foreign substances—such as metal, glass, and plastics—which have been found in tobacco products," FDA said in its release. "The proposed rule would also help address issues related to inconsistencies between e-liquid product labeling and the actual concentrations in e-liquids; such variability can be misleading to consumers, potentially intensifying addiction and exposure to toxins."

"The FDA says there have been inconsistencies between what’s in e-cigarettes and what’s on the label," CNN reports. Gregory Conley, director of legislative and external affairs for the American Vapor Manufacturers Association, told CNN he was disappointed by the timing of the proposed rule.

“The vaping industry has tried in vain for more than a decade to work with FDA on sensible manufacturing standards, only to be ignored while the agency recklessly vilified nicotine vaping,” Conley told CNN in an email. “It is disappointing, but not at all surprising, that the FDA would wait to propose these regulations until it had already committed itself to banning 99.99 percent of the vaping market. The millions of Americans who rely on vaping to stay off cigarettes could benefit from the FDA’s proposal, but only if the agency stops thumbing its nose at its critics and starts to regulate the category in good faith.”

The FDA will hold a public hearing April 12 about the proposed rule.